


Health NGO millions: Key results poor

By RALPH FOLDS
Central Australian Aboriginal Congress has been operating for decades and receives enormous public funding.
Its 2025 income was well over one hundred million dollars, including $83m in grants and contributions. Only 11% came from Medicare and practice incentive payments.
The report recently commissioned by Congress makes sweeping claims about transformation of its health system in Central Australia. But do the measurable health outcomes justify the scale of those claims and expenditure, including $69m for employees benefits?
Making History: Transforming Aboriginal Health in Central Australia 1973–2023 is an impressive historical document, and much of the history it records is genuinely remarkable.
There is no disputing that Aboriginal health outcomes improved dramatically over 50 years covered by the report.
Aboriginal male life expectancy in Central Australia rose from 47.3 years in 1975–77 to 65.6 years in 2014–18 — an increase of 18.3 years but still well below the Australian figure of 81.1 years (ABS). Congress deserves credit for the contribution it made to those gains in The Centre.
But there is a crucial qualification.
The report's headline life-expectancy comparison ends in 2014–18. Its infant-mortality comparison also ends in 2014–18, while its data on babies who were small for their gestational age end in 2016.
More significantly, the report's analysis of premature mortality tells a less encouraging story. Its Years of Life Lost data extend to 2018, but the report says the substantial reduction occurred during the 2000s and that no further gains were made after 2010 – a time of health progress for a lot less money.
A Congress submission states: “In this era, Congress had an annual budget of less than $5m per year as ATSIC had to try to fund everything in Aboriginal communities, from health services to houses to community development.”
Today Congress has a budget twenty times greater.
That matters because the report is presented as a history of Aboriginal health transformation through to 2023. Yet some of its most important measures of health outcomes either stop well before 2023 or show that improvement had already stalled more than a decade earlier.
The report therefore provides compelling evidence of the progress achieved in earlier decades. It provides considerably less evidence about whether that progress has continued in Central Australia since 2018 — and particularly whether health outcomes have improved during the period in which Congress has received substantially increased government funding.
That raises an obvious question: What happened after 2018 — and, for some of the most important measures, after 2010?
History is not the same thing as evidence of current performance.
For an organisation that has grown enormously in size, reach and resources, that distinction matters. The question is no longer simply what happened to Aboriginal health over the past 50 years.
It is what has happened in recent years as Congress has expanded — and what measurable improvement can be attributed to the services it provides.
The data have moved on, and there is no shortage of more recent health information.
Diabetes is an obvious test of whether Aboriginal health is being transformed.
Research published in BMJ Open found that in 2018–19, diabetes affected 39.5% of Aboriginal adults in Central Australia. Across all ages, prevalence was 23%. The researchers described the burden of diabetes in remote Aboriginal communities as “immense and growing”.
That is an extraordinary disease burden. Diabetes contributes to kidney disease, cardiovascular disease, blindness, amputations and premature death.
More recent evidence shows some improvement in aspects of diabetes management nationally. But there is no comparable evidence showing that Central Australia's extraordinarily high diabetes burden has been substantially reduced.
Indeed, Northern Territory Aboriginal Health Key Performance Indicator data show that diabetes control deteriorated between 2018 and 2021. The proportion of tested clients with type 2 diabetes achieving an HbA1c of 7% or less fell from 37.2% to 34%, while the proportion with very poor control — HbA1c of 10% or higher — increased from 24.1% to 27%.
These are NT-wide Aboriginal health figures, not Congress-specific or Central Australia-specific figures, so they cannot by themselves establish Congress's performance. But neither do they provide evidence of an improvement in diabetes control across the NT Aboriginal health system during those years.
The important question is therefore not simply how many people have diabetes. It is whether patients with diabetes are becoming healthier: Whether blood-sugar and blood-pressure control are improving, whether kidney disease is being prevented, whether appropriate screening and treatment are being delivered, and whether serious complications are declining.
Kidney disease provides another measure.
The latest Australian Institute of Health and Welfare data show an enormous continuing burden of chronic kidney disease among First Nations people. In 2022–24, an estimated 101,500 First Nations adults — 19% — had biomedical signs of chronic kidney disease, compared with 18% in 2012–13.
But national figures cannot answer the more important question for Central Australia: is the burden of kidney disease actually falling here?
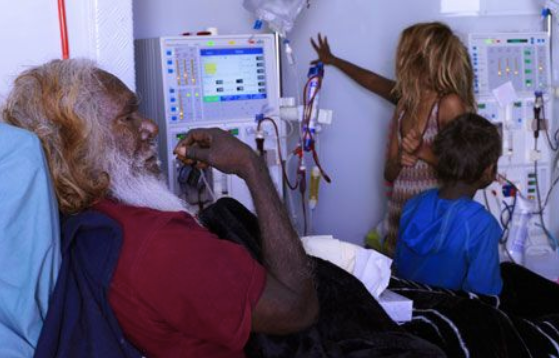
ABOVE: The famed Western Desert artist Patrick Tjungurrayi having dialysis in the Purple Truck’s mobile dialysis unit at his home community Kiwirrkurra in WA, as reported by the ALICE SPRINGS NEWS in December, 2013. Congress has an MoU with Purple House and other health providers, and describes Purple House as a collaborative health-care organisation.
The treatment burden alone is striking. In 2023–24, dialysis as the principal diagnosis accounted for 275,000 hospitalisations among First Nations people — 40% of all hospitalisations in that population. These are hospitalisations, not individual people, so the figure reflects the enormous ongoing demand for dialysis treatment.
Central Australia has long experienced a particularly heavy burden of kidney disease. There has been genuine progress in treating kidney failure: The Australian Institute of Health and Welfare (AIHW) reports that survival rates for dialysis in Central Australia have improved dramatically over the past two decades, going from the worst to the best in Australia.
But treating kidney failure is not the same as preventing it.
If Congress and other health services are claiming continuing transformation, the community should therefore be able to see recent Central Australian outcome data showing whether kidney disease is being detected earlier, whether its progression is being slowed, and whether fewer people are ultimately reaching kidney failure and requiring dialysis.
That is a different question from whether dialysis services themselves have improved. And it is precisely the kind of outcome data needed to demonstrate whether the underlying burden of disease is actually being transformed.
Potentially preventable hospitalisations provide another revealing measure.
AIHW defines these as hospitalisations for conditions where appropriate and timely preventive care or early disease management in the community can potentially prevent the need for hospital treatment. The measure is not a simple scorecard for an individual health service.
AIHW cautions that rates are influenced by many factors, including disease burden, remoteness, socioeconomic disadvantage and access to healthcare. A high rate can reflect poorer non-hospital care, but it can also reflect a greater underlying need for hospital treatment.
But that does not make the figures irrelevant.
According to the latest AIHW data, in 2023–24 Alice Springs recorded 9,700 potentially preventable hospitalisations per 100,000 people — the highest rate among the Statistical Area Level 3 areas reported by AIHW.
That is an extraordinary figure.
It does not prove that Congress is responsible for the rate, because the Alice Springs SA3 population includes people who use many different health services. Nor can it disentangle the effects of remoteness, poverty, disease burden and the broader health system.
But Congress operates at the heart of Aboriginal primary healthcare in Central Australia. After decades of community-controlled primary healthcare, and after substantial expansion in services and resources, it is entirely reasonable to ask a more specific question.
What do Congress's own data show about whether its patients are experiencing fewer potentially preventable hospitalisations and better health outcomes?
(SA3 is a geographic region defined by the Australian Bureau of Statistics. It groups smaller areas together to show regional data. Each SA3 usually has 30,000 to 130,000 people.)
This brings us to a central weakness in assessing Congress's performance: The lack of publicly available outcome data that allows the community to determine whether its substantial investment in Aboriginal primary healthcare is translating into better health outcomes.
Congress's annual reports provide an extensive account of its activities, services and performance measures. But activity is not the same as outcome.
The critical question is not simply how many consultations were provided, how many patients were seen or how many programs were delivered.
It is whether people are healthier as a result.
Congress's 2024–25 Annual Report provides extensive information about its activities and selected clinical performance measures. It reports consultations and episodes of care, health checks, cardiovascular risk, diabetes care plans, HbA1c testing for blood sugar control and the proportion of clients with HbA1c below 7%.
Those measures are important. But they do not, on their own, provide a comprehensive picture of whether the health of Congress patients is improving over time.
The National Key Performance Indicators (nKPIs) system shows that a more sophisticated approach is possible.
The nKPI collection began in 2012 and now receives data from more than 200 First Nations-specific primary healthcare organisations across Australia.
It includes both measures of what healthcare organisations do — such as screening and testing — and measures of the health status and management of the people they serve, including indicators of chronic disease.
At June 2025, 220 organisations were reporting to the nKPI collection.
The system demonstrates that primary healthcare organisations can be assessed not simply on how many services they deliver, but on measures of the health and clinical management of the people they serve.
Congress already collects some of this information. Its 2024–25 Annual Report, for example, reports three years of HbA1c testing and blood-sugar control data.
What is missing is a comprehensive, easily understood Central Australian health-outcomes scorecard that allows the community to see whether those results are improving over time.
Congress could publish a rolling annual scorecard showing not simply how many people it saw or how many services it delivered, but what happened to the health of the people it serves.
For example: Are diabetes control, blood-pressure control and kidney screening improving?
Are fewer patients developing serious complications?
Are potentially preventable hospitalisations falling among Congress patients?
Are outcomes among Congress patients improving faster than comparable populations?
And, crucially, are those results improving year after year?
That would provide a much clearer measure of health outcomes — and a much stronger basis for accountability.
There is another important qualification to Making History.
The historical improvement in Aboriginal health cannot be treated as a controlled experiment measuring the contribution of Congress. Congress operates within a much larger health system. Alice Springs Hospital has changed.
Government health expenditure has increased. Clinical standards have changed. Other Aboriginal organisations provide healthcare. Public-health policies have changed. And housing, education, income, alcohol use and many other social determinants influence health outcomes.
Congress deserves credit for its contribution. But the size of that contribution cannot be established simply by showing that Aboriginal health improved during the decades in which Congress operated.
That is why Congress's contribution needs to be demonstrated through outcomes.
Making History may be right about the past, and the historical improvements it documents are real and deserve recognition.
But its major headline measures do not provide a sufficiently current picture of Central Australian health. Its life-expectancy and infant-mortality comparisons end in 2014–18.
Its analysis of premature mortality reports substantial gains between 1999 and 2010 — but says no further gains were made after 2010. The report does contain some more recent measures, including alcohol-related hospitalisation data extending to 2021, but these still do not provide a comprehensive picture of Central Australian health outcomes through 2025 or 2026.
The contemporary evidence shows that major health problems remain.
Diabetes remains extraordinarily prevalent in Central Australia. Chronic kidney disease remains a major burden. Kidney failure imposes a huge treatment burden on First Nations communities.
And in 2023–24, Alice Springs had the highest rate of potentially preventable hospitalisations of any SA3 reported by AIHW — 9,700 per 100,000 people.
None of these figures, by themselves, proves that Congress has failed. But they demonstrate why historical achievements are not enough to answer the contemporary question.
And a framework for modern health-performance measurement already exists.
The national nKPI system collects both measures of healthcare activity and measures relating to the health status and management of patients. Congress itself already reports some recent clinical outcomes, including measures of diabetes control and continuity of care.
The issue is that these figures are not brought together into a comprehensive, easily understood longitudinal scorecard showing whether the health of Congress patients is actually improving over time.
There is therefore no compelling reason to assess contemporary performance primarily through historical achievements.
Congress has certainly made history.
But the unanswered question is whether it is transforming Aboriginal health today — as the title of its report suggests.
What has happened to Aboriginal health in Central Australia in recent years as Congress has expanded — and what measurable improvement can be demonstrated from the substantial resources now devoted to it?
That is a legitimate question for taxpayers.
It is a legitimate question for Aboriginal communities. And it is a question Congress should welcome answering.
Congress has made history. The question now is whether it is transforming Aboriginal health today.
Until that can be demonstrated through current health outcomes, claiming that transformation is happening is premature.
PHOTO at top: Cover of the report.